

What physiological triggers cause an itching sensation in a healing wound?
An itching sensation, known medically as wound pruritus, is a common biological response triggered during the inflammatory and proliferative phases of wound healing and repair. As new tissue forms, mast cells release histamines and inflammatory cytokines into the wound bed, stimulating localized C-fiber nerve endings that transmit itch signals to the central nervous system.
Additionally, mechanical tension caused by myofibroblast contraction and new skin cell migration across dry or scabbed tissue physically irritates surrounding nerve pathways, creating a persistent urge to scratch.
While itching is frequently a benign sign that vascularization, collagen synthesis, and re-epithelialization are actively occurring, severe or worsening pruritus can also indicate dry skin (xerosis), contact dermatitis from adhesives or topical ointments, or underlying bacterial infection.
Identifying the precise physiological trigger ensures patients manage discomfort safely without disrupting fragile new tissue.
Biological Drivers of Wound Pruritus
- Histamine and Cytokine Release: Mast cells entering the wound bed during the proliferative phase release histamine, prostaglandin E2, and interleukins to orchestrate tissue repair. These neurochemical mediators directly stimulate unmyelinated C-fiber itch receptors in the dermal layers.
- Nerve Fiber Regeneration and Hyper-Excitability: As severed peripheral nerve fibers re-grow into regenerating granulation tissue, they experience temporary hyper-excitability, sending erratic action potentials to the spinal cord that the brain interprets as itching.
- Mechanical Tension and Tissue Contraction: Specialized cells called myofibroblasts contract the wound margins to reduce total surface area. This mechanical pulling creates physical stress on adjacent uninjured skin cells and nerve pathways, inducing localized itch.
- Epidermal Desiccation and Crust Formation: When a wound bed or periwound skin dries out, stiff scabs or desiccated skin edges crack during normal movement, irritating superficial sensory nerve endings.
- Contact Sensitization and Allergic Reaction: Sensitivities to topical antibiotics (such as neomycin or bacitracin), medical tapes, acrylic adhesives, or preservatives in wound dressings frequently manifest as intense localized pruritus accompanied by periwound redness.
How can clinicians and patients differentiate normal healing itch from signs of infection or allergic dermatitis?
Differentiating normal physiological healing itch from pathological complications requires evaluating the intensity, duration, visual characteristics, and accompanying symptoms around the wound site.
Normal healing itch is typically mild to moderate, intermittent, localized strictly to the wound margins, and decreases as epithelialization completes. In contrast, itching caused by surgical site infection, contact dermatitis, or bioburden overload is intense, persistent, spreads to surrounding skin, and is accompanied by systemic or localized inflammatory signs.
Recognizing these clinical distinctions helps prevent serious complications or misinterpreting allergic reactions as routine healing.
| Clinical Feature | Normal Physiological Healing Itch | Contact Dermatitis / Adhesive Allergy | Localized Infection / Bioburden Overload |
|---|---|---|---|
| Itch Onset & Intensity | Mild to moderate; intermittent, noticeable during dressing changes or tissue contraction[cite: 26] | Severe, intense, and continuous; develops rapidly after applying new tape, dressing, or ointment[cite: 26] | Moderate to severe; persistent throbbing or burning itch that progressively worsens[cite: 26] |
| Visual Periwound Appearance | Healthy pink epidermal edges; clean granulation tissue; minimal clear exudate[cite: 26] | Defined red rash matching dressing or tape borders; micro-vesicles, papules, or peeling skin[cite: 26] | Spreading dark redness (erythema), localized swelling (edema), skin warmth, and induration[cite: 26] |
| Exudate & Odor | Minimal, clear serous or light serosanguinous fluid; odor-free[cite: 26] | Variable exudate; clear fluid leaking from contact blisters; no foul odor[cite: 26] | Moderate to heavy purulent (thick yellow/green) drainage; foul or sweet odor[cite: 26] |
| Pain Level | Low; minor itch-discomfort easily managed with light pressure[cite: 26] | Burning sensation combined with intense localized surface itching[cite: 26] | Elevated throbbing pain, localized tenderness, or sharp pain radiating from deep tissue[cite: 26] |
| Systemic Symptoms | None; localized strictly to the healing tissue boundary[cite: 26] | None; restricted to contact surface of allergen[cite: 26] | Spiking fevers, chills, elevated heart rate, and fatigue indicating systemic spread[cite: 26] |
What are the most effective clinical and at-home strategies to relieve itching safely during wound care?
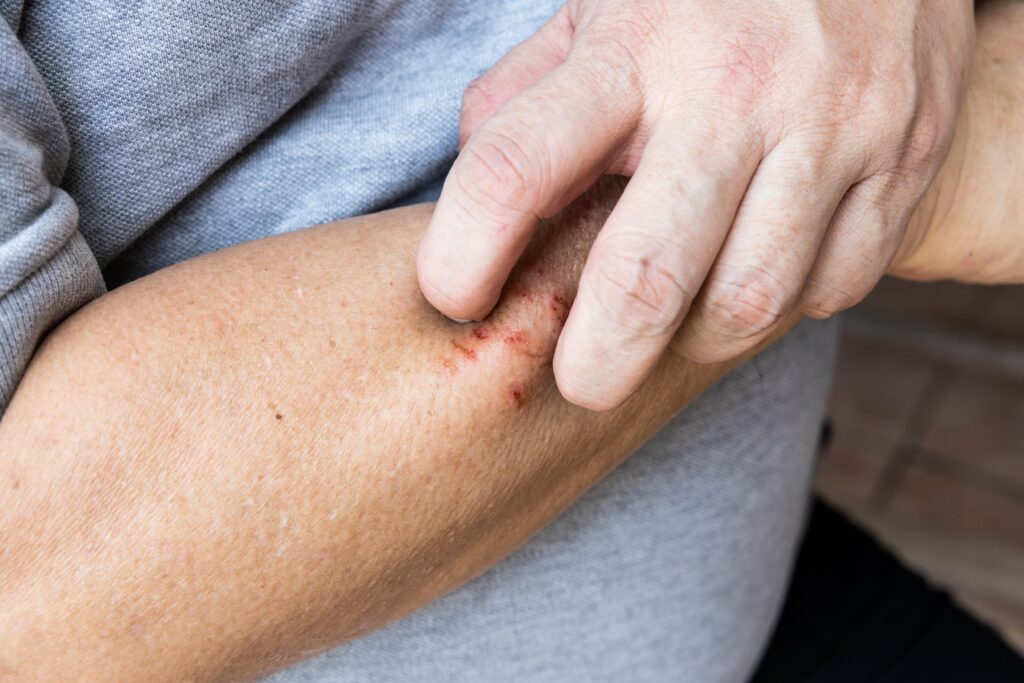
Relieving wound itching safely requires protecting fragile new tissue while suppressing histamine release, maintaining optimal moisture balance, and cooling irritated nerve endings. Scratching a healing wound must be strictly avoided, as mechanical disruption tears delicate epithelial cells, re-opens closed wound margins, introduces pathogenic bacteria from fingertips, and drastically increases the risk of hypertrophic scarring or chronic wound recurrence.
Implementing targeted clinical interventions and non-pharmacological relief techniques allows patients to manage pruritus effectively without compromising tissue integrity.
Step 1: Maintain Moisture (Apply barrier creams or hydrogels to prevent dryness)
│
Step 2: Cool Nerve Endings (Apply cold compresses or cool air over intact dressings)
│
Step 3: Modify Dressings (Switch to hypoallergenic silicone tapes or moisture-balancing foams)
│
Step 4: Pharmacological Management (Utilize oral antihistamines or prescribed topical steroids)
Evidence-Based Itch Relief Protocols
- Cool Compresses and Thermal Therapy: Applying a clean, cold gel pack or ice pack wrapped in a sterile towel over intact secondary dressings for 10–15 minutes constricts local capillaries and numbs superficial sensory nerve fibers, temporarily shutting down itch signal transmission.
- Moisture Preservation and Barrier Creams: Applying medical-grade emollients, petrolatum-based barriers, or hydrogel dressings to intact periwound skin prevents xerosis and maintains tissue flexibility, eliminating mechanical pulling on nerve endings.
- Hypoallergenic and Silicone-Based Dressings: Transitioning from harsh acrylic adhesives to soft silicone borders, non-adherent contact layers, or tubular retention bandages eliminates chemical irritation and mechanical shear during dressing removals.
- Oral Antihistamines: Utilizing over-the-counter or prescription oral H1-receptor antagonists (such as cetirizine, loratadine, or diphenhydramine) blocks systemic histamine binding, significantly reducing itch perception, especially at night.
- Light Pressure and Vibration: Gently pressing a clean, gloved hand or sterile dressing pad over the itching area applies light pressure, which travels along faster A-beta nerve fibers to override the slower C-fiber itch signals in the spinal cord (Gate Control Theory).
What role does dressing selection play in controlling or exacerbating wound pruritus?
Dressing selection plays a critical role in managing wound pruritus because improper dressings can desiccate the wound bed, cause exudate pooling, or trigger allergic contact sensitivity. Modern moisture-retentive dressings—such as hydrogels, hydrocolloids, and bordered foam dressings—regulate fluid levels, protect regenerating nerve endings from atmospheric exposure, and prevent skin cracking, thereby suppressing the primary mechanical and environmental triggers of itching.
Matching dressing properties directly to the wound’s moisture requirements prevents moisture-related skin breakdown and chemical contact allergies.
Dressings That Reduce Itching
- Silicone-Bordered Polyurethane Foam Dressings: Absorb excess exudate while providing gentle, non-traumatic adhesion that prevents epidermal stripping and contact dermatitis on sensitive periwound skin.
- Hydrogel Dressings: Donate essential moisture to dry, scabbed, or low-exudate wounds, cooling exposed nerve endings and softening rigid tissue edges.
- Medical-Grade Honey Dressings: Provide natural anti-inflammatory and osmotic action that calms localized tissue swelling while delivering broad-spectrum antimicrobial protection.
- Impregnated Contact Layers: Non-adherent porous layers placed directly over raw tissue prevent secondary dressings from sticking to regenerating epithelium, eliminating painful tearing and subsequent itching during changes.
Dressing Practices That Cause or Worsen Itching
- Harsh Medical Tapes and Acrylic Adhesives: Repeated application and removal of aggressive adhesive tapes cause mechanical epidermal stripping, triggering severe localized inflammatory dermatitis.
- Under-Absorbent / Over-Occlusive Dressings: Allowing heavy wound fluid to pool against healthy periwound skin causes maceration, fungal overgrowth, and intense burning itch.
- Frequent Unnecessary Dressing Changes: Disturbing the wound bed prematurely exposes regenerating tissue to air currents, temperature drops, and mechanical friction, triggering immediate nerve irritation.
When does severe wound itching indicate a medical complication requiring clinical intervention?
Severe wound itching indicates a medical complication requiring immediate clinical intervention when it is accompanied by spreading redness, localized heat, purulent drainage, skin blistering, or systemic fever. While mild itching is an expected part of tissue repair, unmanageable or sudden-onset pruritus often signals localized surgical site infection, bacterial biofilm colonization, contact hypersensitivity, or chronic venous stasis dermatitis.
Failing to address complicated wound pruritus can lead to compulsive scratching, wound dehiscence, secondary bacterial infection, and delayed healing timelines.
Red-Flag Symptoms Accompanying Itching
- Spreading Periwound Erythema: Redness extending more than 2 centimeters beyond the wound margin, suggesting cellulitis or bacterial invasion.
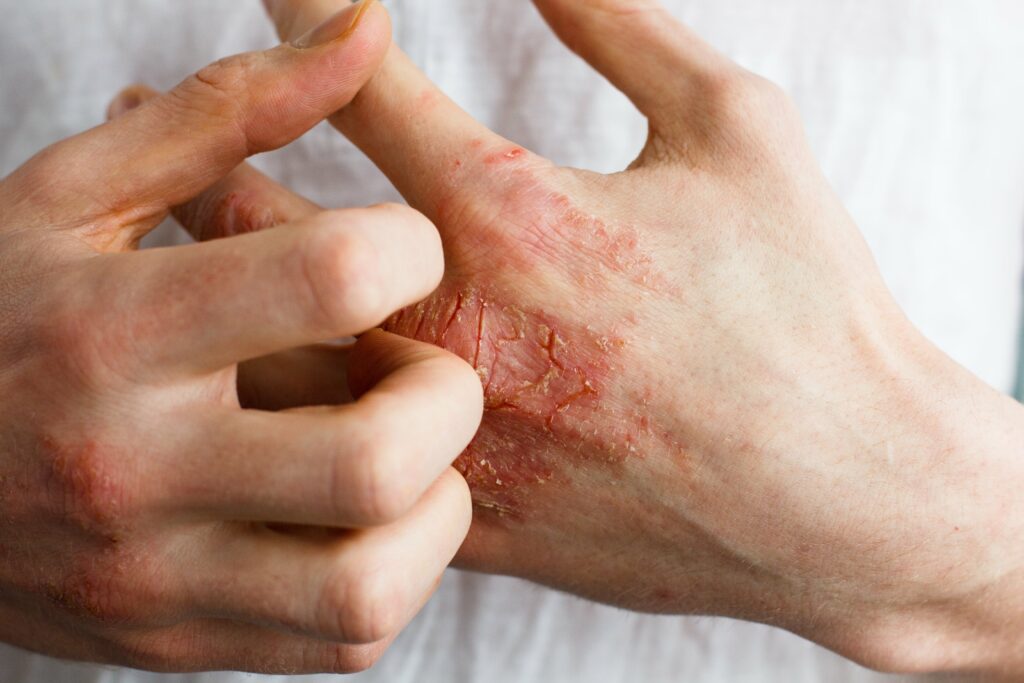
- Severe Blistering or Peeling (Phlyctenules): Clear or fluid-filled vesicles forming under adhesive tape borders, indicating severe allergic contact dermatitis or friction injury.
- Purulent Exudate and Odor: Transition from clear fluid to thick, cloudy, or foul-smelling drainage, pointing to active bacterial infection.
- Failure to Epithelialize / Stalled Healing: Wounds that show no edge progression or display friable, overgrowing hypergranulation tissue alongside severe itching.
- Systemic Allergic or Infectious Reactions: Widespread body hives, facial swelling, elevated body temperature, or chills.
How do mobile wound care services help manage wound pruritus and complex healing at home?
Mobile care assists patients dealing with severe wound itching by delivering specialized bedside assessments, hypoallergenic dressing adjustments, prescriptive topical therapies, and infection monitoring directly to the patient’s home, assisted living facility, or skilled nursing center.
For homebound, elderly, or mobility-impaired individuals, mobile care eliminates the stress of traveling while ensuring that wound complications causing itch are identified and treated early.
Managing complex wound pruritus requires continuous clinical evaluation to balance moisture levels, eliminate allergen triggers, and prevent secondary infections. Mobile wound care teams deliver this specialized oversight directly at the bedside.
Benefits of In-Home Mobile Care for Managing Pruritus
- On-Site Allergy and Contact Assessment: Licensed wound care specialists evaluate the wound bed and surrounding skin, immediately identifying and replacing irritating tapes, ointments, or adhesives with hypoallergenic silicone alternatives.
- Bedside Infection Control and Culturing: If itching is accompanied by purulent drainage or spreading redness, mobile providers collect wound cultures and prescribe targeted oral or topical antimicrobials on site.
- Prescription of Advanced Moisture-Balancing Dressings: Mobile teams supply and apply specialized hydrogels, silicone foams, and antimicrobial barriers tailored to the patient’s exact exudate level, keeping the wound comfortably hydrated.
- Patient and Caregiver Education: Teaches family members and home health aides safe itch-relief techniques—such as proper cold-pack application, light pressure methods, and gentle periwound skin hydration—preventing damaging scratch trauma.
- Continuous Monitoring and Reduced Readmissions: Regular bedside evaluations ensure that itch-inducing complications are resolved before they cause wound breakdown, keeping high-risk patients recovering safely in their living environment.